
Independent Evidence Review • Updated September 2, 2026
Three respiratory viruses can circulate during the same season, but their vaccines are not interchangeable. This review explains how vaccination developed, what each vaccine is designed to do, and what current U.S. guidance says.
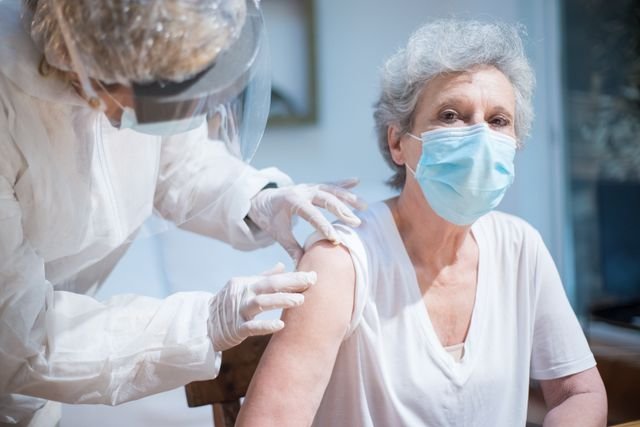
COVID-19, influenza (flu) and respiratory syncytial virus (RSV) can all cause cough, fever or breathing problems, yet they are caused by different viruses. Their risks also differ by age and health status. Vaccines and other immunizations are intended primarily to reduce serious outcomes; they do not promise that every infection will be prevented.
Why vaccination matters
Vaccination trains the immune system to recognize a threat before a person encounters the disease. If exposure later occurs, immune memory can respond faster. Protection may lessen over time, and a virus may change, which is why some vaccines are updated or repeated.
The broader history is important. Vaccination contributed to the global eradication of smallpox, officially certified in 1980, and dramatically reduced diseases such as paralytic polio in the United States. These achievements do not mean every vaccine works identically. Benefits and risks must be studied separately for each product, age group and outcome.
Respiratory vaccines are generally evaluated for outcomes such as medically attended illness, hospitalization or death—not only whether any infection occurs.
Older adults, young infants, pregnant people and people with certain chronic conditions can face greater risk from respiratory disease.
Preventing a portion of urgent visits and hospitalizations can help families, clinicians and health systems during busy seasons.
A short history of the three vaccines
1945 — Influenza: The first flu vaccine was licensed for use in the United States. Because influenza viruses continually change, surveillance and vaccine composition review became a recurring process.
2003 — Nasal flu vaccine: A live-attenuated intranasal influenza vaccine joined injectable options for eligible people.
December 2020 — COVID-19: FDA issued the first U.S. emergency use authorization for a COVID-19 vaccine. Later products and formulations underwent additional authorization or approval review, and compositions have been updated as SARS-CoV-2 evolved.
2023 — RSV: FDA approved the first RSV vaccines for older adults. The United States also introduced maternal RSV vaccination and long-acting monoclonal-antibody protection for infants. The infant antibodies are immunizations, but they are not vaccines.
At-a-glance comparison
| Topic | Flu | COVID-19 | RSV |
|---|---|---|---|
| Main U.S. approach | Routine seasonal vaccination | Current CDC page uses individual-based decision-making | Targeted by age, risk and pregnancy timing |
| Repeated every year? | Yes, generally each season | Depends on current schedule and personal factors | Adult RSV vaccine is not currently annual |
| Infant protection | Age-based vaccine schedule begins at 6 months | Follow the current age/formulation schedule | Maternal vaccine or an infant monoclonal antibody for most infants |
Influenza vaccine: an annually updated defense
CDC’s interim 2026–2027 clinical considerations state that the existing seasonal recommendations remain in effect: annual influenza vaccination is recommended for everyone age 6 months and older who does not have a contraindication. Some children ages 6 months through 8 years may need two doses in a season, depending on vaccination history.
For 2026–2027, U.S. flu vaccines are trivalent, targeting two influenza A components and one influenza B component. The exact strains differ slightly between egg-based and cell-based or recombinant manufacturing platforms. Protection takes time to develop and vaccine effectiveness varies with age, health, circulating viruses and how closely vaccine components match them.
COVID-19 vaccine: guidance must be date-stamped
COVID-19 recommendations have changed repeatedly as population immunity, circulating variants, evidence and available formulations changed. On the CDC page available when this review was prepared, the agency recommends a 2025–2026 COVID-19 vaccine for people age 6 months and older using individual-based decision-making. CDC emphasizes its importance for people age 65 and older, people at higher risk of severe COVID-19, long-term-care residents and people who have never received a COVID-19 vaccine.
This wording should not be assumed to be the final 2026–2027 schedule. Readers should check the current CDC immunization schedule and an appropriate clinician or pharmacist before acting. Prior infection does not create permanent protection, and vaccine protection can also decrease with time. Updated vaccines are intended to improve the match to circulating strains.
RSV vaccine and infant immunization: targeted protection
RSV commonly causes cold-like illness, but it can be serious for infants, older adults and people with certain health conditions. CDC currently recommends one RSV vaccine dose for all adults age 75 and older and for adults ages 50–74 who have increased risk of severe RSV illness. Adult RSV vaccination is not currently an annual vaccination.
To protect infants, CDC describes two principal approaches: maternal vaccination with Pfizer’s Abrysvo during weeks 32 through 36 of pregnancy during the seasonal window, or administration of a long-acting RSV monoclonal antibody to the infant. Most infants do not need both. Nirsevimab and clesrovimab are antibodies—not vaccines—and recommendations depend on age, season, maternal vaccination status and risk.
Can these vaccines be given together?
CDC guidance permits coadministration of many vaccines during the same visit, using different injection sites. However, whether to receive flu, COVID-19 and RSV vaccines together is an individualized decision. Timing, expected reactions, prior vaccine history, pregnancy, medical conditions and convenience can matter. A clinician or pharmacist can check the current product-specific guidance.
Safety, expected reactions and limitations
Common reactions after respiratory vaccination can include soreness, redness or swelling at the injection site, fatigue, headache, muscle aches, chills or fever. They are generally short-lived. Fainting can occur after vaccination, particularly in adolescents, which is one reason observation practices may be used.
Serious allergic reactions are rare but require urgent treatment. Each vaccine has product-specific contraindications, precautions and safety information. Some rare adverse events are monitored after authorization because very large populations can reveal signals that preauthorization trials could not easily detect. Reporting after vaccination does not automatically establish that a vaccine caused an event; regulators evaluate patterns, background rates and clinical evidence.
How to evaluate vaccine claims responsibly
- Check the date. Respiratory-virus recommendations and products change.
- Separate infection prevention from protection against hospitalization or death.
- Ask which population was studied; results in healthy younger adults may not apply to frail older adults or infants.
- Distinguish association from causation in safety reports.
- Prefer CDC, FDA, NIH, state health departments and peer-reviewed studies over unsourced social-media claims.
Bottom line
Flu, COVID-19 and RSV vaccination strategies share a goal—reducing serious respiratory illness—but the schedules are different. Flu vaccination is broadly seasonal, COVID-19 recommendations should be checked against the newest schedule, and RSV vaccination is targeted to specific adult and pregnancy groups, with antibody options for infants. The most reliable decision combines current official guidance with an individual review of age, risk factors and prior immunization history.
References and supporting documents
- CDC. Interim Clinical Considerations for Seasonal Influenza Vaccines, 2026–2027.
- CDC. 2026–2027 Flu Season: U.S. vaccine composition.
- CDC. ACIP Recommendations Summary: Influenza.
- Maloney P, et al. Interim Estimates of 2025–26 Seasonal Influenza Vaccine Effectiveness. MMWR. 2026;75:116–123.
- CDC. Staying Up to Date with COVID-19 Vaccines.
- CDC. Current Epidemic Trends Based on R(t).
- FDA. Pfizer-BioNTech COVID-19 Vaccine Emergency Use Authorization documentation.
- CDC. RSV Vaccine Guidance for Adults.
- CDC. RSV Vaccine Guidance During Pregnancy.
- CDC. RSV Immunization Guidance for Infants and Young Children.
- CDC/ACIP. Use of Pfizer RSV Vaccine During Pregnancy. MMWR. 2023.
- CDC. History of Smallpox and Global Eradication.
- CDC. Vaccine-Preventable Diseases, Immunizations and MMWR.
Editorial note: Official recommendations were checked on September 2, 2026. External guidance may change after publication. Brand names appear only where necessary to distinguish an approved product or recommendation; no endorsement or affiliation is implied.